
I’ll never forget sitting in an emergency room at 2 AM, holding a bill that had three extra zeros I wasn’t expecting.
I was 27, had just switched jobs, and — in the chaos of signing paperwork and setting up direct deposit — I had unknowingly let a 30-day gap slip into my health coverage. The public option I thought I had enrolled in hadn’t kicked in yet. The private plan I’d left behind had lapsed. And the universe, in its infinite sense of humor, chose that window to give me a kidney stone.
That night cost me more than a month’s rent.
If someone had sat me down a year earlier and actually explained — not in insurance-brochure language, but in plain human English — how public and private health insurance work and when to use which, I would have made very different choices. So that’s what this is. The conversation I wish I’d had.
First, Let’s Ditch the Textbook Definitions
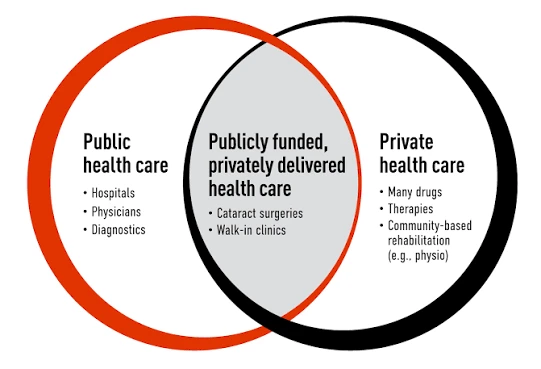
You’ve probably already Googled the basics. Public insurance = government-run. Private insurance = company-run. Okay, sure. But that framing makes it sound like a binary choice, like you’re picking a political side. It’s not that simple, and in many countries, you’re not even choosing one or the other — you’re stacking them, supplementing one with the other, or navigating a hybrid system.
What actually matters is understanding how each one behaves in real life, when you’re sick, broke, confused, or all three at once.
What Public Health Insurance Actually Looks Like
Public insurance goes by different names depending on where you are. In the US, it’s Medicare (for people over 65 or with certain disabilities) and Medicaid (for lower-income individuals and families). In the UK, it’s the NHS. Canada has its provincial health systems. Australia has Medicare (different from the US version). Most of Europe operates on some variation of a national or social insurance model.
Here’s the core promise of public health insurance: you won’t go bankrupt for needing basic medical care. That’s the whole point. It exists because markets, left entirely alone, tend to price sick people out of getting help.
The tradeoff? Wait times. Paperwork. Sometimes limited access to specialists. The experience varies wildly depending on the country, the region, and frankly the specific clinic you walk into.
When I was living abroad for a year in Portugal, I used the public health system there for a minor procedure. I waited about three weeks for a non-urgent appointment — which felt long — but I walked out paying nothing. Not a co-pay. Not a deductible. Nothing. I honestly stood at the exit for a moment waiting for someone to hand me a bill.
That experience changed how I thought about public systems. The wait was real. The cost savings were also very real.
What Private Health Insurance Actually Looks Like
Private insurance is sold by companies — think Aetna, BlueCross, Bupa, AXA, and hundreds of others depending on your country. You pay a monthly premium. In exchange, the insurer covers some or all of your medical costs, depending on your specific plan.
The appeal is obvious: faster access, more provider choices, and often nicer facilities. If you’ve got a good employer-sponsored plan, private insurance can feel almost magical — you go to your preferred doctor, pay a small co-pay, and go home.
But here’s what the brochures don’t highlight: private insurance is a business. The company makes money when you pay premiums and don’t use services. That creates incentive structures that can work against you when you actually get sick.
I learned this the hard way when I tried to get a referral for a specialist. My plan technically covered it — but only if I went through my primary care physician first, only if the specialist was “in-network,” and only after meeting an annual deductible I hadn’t even heard of before that phone call. Three weeks and four phone calls later, I had my appointment. The specialist was worth it. The process was not.
The Key Differences That Actually Matter
Let me break down the real distinctions — the ones that affect your daily life, not just your tax return.
Cost Structure
Public insurance is usually funded through taxes. You may pay nothing at the point of service, or a very small co-payment. The “cost” is baked into your paycheck or your country’s tax system before you ever see a doctor.
Private insurance works on premiums. You pay monthly, often quarterly. On top of that, you typically have a deductible (amount you pay before insurance kicks in), co-pays (flat fee per visit), and co-insurance (percentage you pay after the deductible). It adds up fast. A “good” private plan in the US might still leave you responsible for $4,000–$8,000 per year out of pocket before the insurer covers everything.
Speed and Access
This is where private usually wins. Private plans often let you see specialists directly, get faster appointments, and access hospitals with shorter queues. If you need a non-urgent MRI, a private plan might get you in next week. The public system might be six weeks out.
That said, in emergencies? Public systems typically don’t discriminate. You’ll get care. The wait-time gap usually shows up for elective, specialist, and preventive care.
Coverage Breadth
Public systems tend to cover “medically necessary” care. Private plans vary enormously. Some cover dental, vision, mental health, physiotherapy, and alternative treatments. Others cover the bare minimum. Always read the fine print — specifically what’s excluded, not just what’s included.
Geographic Flexibility
If you travel frequently or live between countries, private international health insurance is often the only practical option. Public health systems are tied to residency and citizenship. The moment you cross a border, most public coverage gets complicated fast.
When Public Insurance Is the Smarter Choice
Let me give you some real scenarios where public wins:
You’re young, healthy, and broke. If you’re in your 20s and rarely see a doctor, paying high private premiums is often a bad deal. If your country offers a public option, it covers the catastrophic stuff (the kidney stone, the broken arm) without draining your bank account monthly.
You have a chronic condition that requires consistent, ongoing care. Public systems often have better long-term case management for conditions like diabetes, heart disease, or certain cancers. The continuity of care can be genuinely better — you’re not dropped when you change jobs or miss a premium payment.
You’re navigating a low-income period. In the US, losing your job can make you eligible for Medicaid, which in many states is genuinely comprehensive. I’ve seen people get better coverage through Medicaid than through employer plans that required jumping through a dozen hoops.
When Private Insurance Is Worth Every Penny
And here’s when private pulls ahead:
You want control over who treats you. Public systems assign you doctors. Private insurance, especially premium plans, lets you choose your specialist, your surgeon, your hospital. That matters a lot when you’ve got a complicated condition and you want the specific expert.
You’re running your own business or freelancing. Without employer-sponsored coverage, the private market is your only real option in many countries. Yes, it’s expensive. But the alternative — gambling with no coverage — is almost always worse. I freelanced for two years and paid for private coverage the entire time. I resented the bill every month until I actually needed it.
You need specific treatments that public systems deprioritize. Cosmetic surgery, cutting-edge cancer treatments still in limited rollout, certain fertility procedures, high-end mental health therapy — public systems often don’t cover these or have long queues. Private plans (especially at premium tiers) can open those doors.
You travel internationally for work or extended periods. International private health insurance from companies like Cigna Global, Allianz, or BUPA International exists specifically for this. It’s the only sensible option if you spend significant time outside your home country.
The Hybrid Reality: Using Both
Here’s something most people don’t realize: in many countries, public and private aren’t mutually exclusive. You can — and often should — use both.
In Australia, for example, residents get Medicare (public) automatically, but many people also take out private hospital cover. The Medicare system handles your GP visits and many specialist appointments. The private plan covers private hospital rooms, shorter surgical waits, and additional services.
In the UK, some people have NHS coverage as their baseline but pay for private healthcare for specific needs like faster specialist access. They might see an NHS GP regularly but pay out of pocket (or through private insurance) for a quicker knee surgery than the NHS waitlist would offer.
The strategy I’ve seen work best for most people: use public insurance as your safety net and private insurance to fill the specific gaps that matter most to you.
Figure out what you actually use healthcare for. If it’s mostly GP visits and the occasional prescription, a basic public-plus-top-up structure might be all you need. If you have kids, a complex health history, or you value speed above all else, a more robust private plan starts making sense.
Mistakes I’ve Seen People Make (Including Me)
Letting coverage lapse during job transitions. I mentioned my own kidney stone disaster. Don’t be me. When you leave a job, find out your exact coverage end date and start your next coverage the same day or earlier. In the US, COBRA lets you continue your employer plan temporarily — it’s expensive, but cheaper than an uninsured ER visit.
Assuming “covered” means “paid for.” Private insurance especially loves this trick. Yes, your policy covers MRIs. But did you hit your deductible? Is the radiologist in-network? Did you get pre-authorization? Each of those questions is a potential out-of-pocket expense hiding behind the word “covered.”
Ignoring the network. Every private plan has a network of doctors and hospitals they’ve contracted with. See someone outside that network, and you’re often paying dramatically more — sometimes paying the entire bill yourself. Before your first appointment with any new provider, call your insurance company and ask directly: “Is Dr. X in-network for my specific plan?”
Not using preventive care. Most health insurance — public and private — covers preventive care at zero or very low cost. Annual checkups, screenings, vaccines. People skip these because they feel fine, then end up with a larger problem later that costs far more. Use your preventive benefits. That’s money left on the table otherwise.
Choosing a plan based on the premium alone. The monthly premium is the most visible number, so people optimize for it. But a plan with a $150/month premium and a $6,000 deductible might cost you more in a bad year than a $300/month plan with a $1,500 deductible. Run the math on the worst-case scenario, not just the monthly cost.
How to Actually Choose: A Practical Framework
If you’re sitting there trying to figure out which direction to go, here’s how I’d think through it:
Step 1: Know what you have access to. Start with your baseline. Are you eligible for a public program in your country? What does your employer offer, if anything? What’s the private market in your area look like? Tools like Healthcare.gov (US), the NHS website (UK), or your country’s equivalent can map this out quickly.
Step 2: Estimate your actual healthcare usage. Be honest. Do you see a doctor once a year for a physical, or do you have ongoing appointments for chronic conditions? Do you take regular prescriptions? Do you have kids who get sick often? Your usage pattern should drive your plan choice.
Step 3: Run the total cost, not just the premium. For any plan you’re considering, calculate: annual premium + estimated deductible + typical co-pays + out-of-pocket maximum. Then compare that number across your options. The right plan for a healthy 30-year-old looks very different from the right plan for a family of four.
Step 4: Check the network for your specific doctors. If you have a doctor you love, make sure they’re in-network before you commit to any private plan. Most insurance company websites have a provider search tool.
Step 5: Look at drug coverage separately. If you take prescription medications, verify they’re covered under the plan’s formulary (their list of covered drugs) and at what cost tier. This alone can swing the math significantly.
Step 6: Think about what’s next for you. Planning to have a baby? Make sure maternity is covered well. Thinking about moving abroad for a year? Look at international coverage. Your life plan should inform your coverage plan.
The Honest Bottom Line
There’s no universally correct answer here. Public insurance provides a safety net that prevents real financial disaster. Private insurance provides speed, choice, and access to things public systems don’t cover. Most people who navigate this well use them in combination — consciously.
The worst thing you can do is what I did: assume you’re covered when you’re not, or understand your coverage so vaguely that the fine print blindsides you at the worst possible moment.
Take an hour this month. Pull up your current policy — or the plan you’re considering — and actually read the summary of benefits. Call the insurance company with specific questions. Ask your HR department to walk you through your options. It’s genuinely boring work. It’s also the kind of boring work that protects you from very expensive surprises.
Because no one wants to be sitting in an emergency room at 2 AM doing the math on a bill they never saw coming.
Have questions about navigating your specific health insurance situation? Drop them in the comments — I try to respond to every one.



